


Victorine Njong
October 11, 2026
Assisted Living Emergency Care Protocols: A Step-by-Step Guide
Table of Contents
- Why Emergency Care Protocols Matter in Assisted Living
- Building Your Assisted Living Emergency Preparedness Plan
- Assisted Living Medical Emergency Procedures: Immediate Response Steps
- Developing an Assisted Living Fire Evacuation Plan
- Creating and Maintaining an Assisted Living Emergency Contact List
- Staff Training, Drills, and Readiness
- Emergency Supplies, Equipment, and Continuity of Care
- Post-Incident Documentation and Quality Improvement
- Frequently Asked Questions
Last Updated: October 11, 2026
Why Emergency Care Protocols Matter in Assisted Living
Emergency care protocols are the backbone of safe, responsive assisted living. A clear plan means staff know exactly what to do, families get notified quickly, and residents receive appropriate care without confusion or delay. (Source: guidelines from the Centers for Medicare & Medicaid Services (CMS))
Facilities without clear emergency procedures waste critical time deciding who calls 911 and what to communicate.
Emergency care protocols protect your facility legally, satisfy regulatory requirements, and give families peace of mind that their loved one is in capable hands.
This guide walks you through building and maintaining emergency care protocols that work in real situations, not just on paper.
Building Your Assisted Living Emergency Preparedness Plan
Your emergency preparedness plan identifies potential crises and your facility’s response. It covers medical emergencies, fires, severe weather, power outages, and staffing gaps.
Risk Assessment and Hazard Identification
Identify likely emergencies by walking through your building, asking staff about concerns, and reviewing past incidents.
Common hazards in assisted living include:
- Medical emergencies (falls, cardiac events, stroke, choking, allergic reactions)
- Fires and evacuation challenges
- Severe weather (storms, flooding, extreme heat or cold)
- Power outages affecting medication storage or medical equipment
- Staffing shortages during illness or holidays
- Resident elopement or behavioral crises
- Water or food contamination
For each hazard, document likelihood, who it affects most, available resources, and response gaps. This assessment drives every other decision in your plan.
Establishing Clear Roles and Responsibilities
Assign clear roles before an emergency: Emergency Coordinator (decisions, 911 calls, family contact), Medical Responder (assessment, first aid), Communicator (calls, notifications, documentation), Safety Officer (resident checks, evacuation), Resource Manager (medications, records, supplies), and Support Staff (comfort, mobility assistance). Smaller facilities may combine roles. Document assignments in writing and update when staff changes.
Assisted Living Medical Emergency Procedures: Immediate Response Steps
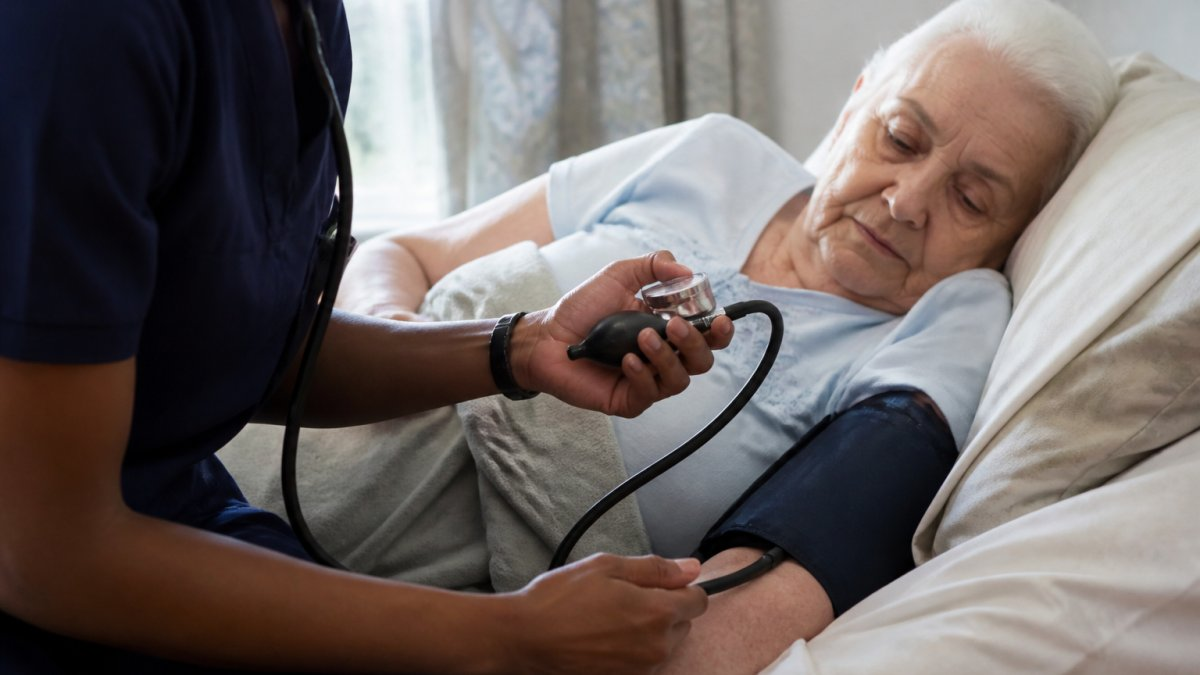
Your response in the first five minutes sets the trajectory for any acute medical event: chest pain, difficulty breathing, loss of consciousness, severe bleeding, choking, falls with injury, or sudden behavioral changes.
Assessing the Resident’s Condition
Quickly assess: (1) Check responsiveness by speaking and gently tapping. (2) Check breathing and pulse for no more than 10 seconds. (3) Look for obvious injury, bleeding, vomiting, unusual skin color, or difficulty speaking/moving. (4) Ask conscious residents what they feel. (5) Check for medical alert bracelets or DNR orders. Document observations and exact time found.
When to Call 911 vs. Contact the Resident’s Clinician
This is the hardest decision in emergency care. Call 911 immediately if:
- The resident is unconscious or unresponsive
- Difficulty breathing or shortness of breath
- Chest pain or pressure
- Severe bleeding that doesn’t stop with direct pressure
- Signs of stroke (facial drooping, arm weakness, speech difficulty)
- Choking that doesn’t clear with back blows or abdominal thrusts
- Severe allergic reaction (swelling, difficulty breathing, hives spreading)
- Suspected poisoning or overdose
- Severe injury from a fall
- Seizure activity
- Severe abdominal pain
- Any situation where you’re unsure but the resident appears to be in danger
Contact the resident’s clinician instead of 911 if:
- The resident has a fever but is alert and breathing normally
- Minor cuts or scrapes
- Mild stomach upset or diarrhea
- Medication side effects (mild dizziness, nausea)
- Behavioral changes without physical symptoms
- Fall with no visible injury and resident is alert and moving normally
- Urinary symptoms without fever
When contacting the clinician, describe observations: alert status, symptoms, vital signs, and medication history. The clinician will advise whether to send to the emergency department, clinic, or monitor at home. Document the decision and clinician’s name.
Monitoring and Documentation During Treatment
While waiting for help: keep the resident calm and comfortable, monitor breathing and consciousness, keep other residents away, gather medications and medical records, note appearance and changes, record vital signs if trained, and document exact times. When paramedics arrive, hand over documentation and describe what you observed and when.
Developing an Assisted Living Fire Evacuation Plan
Your fire evacuation plan must account for residents with mobility limitations, cognitive impairment, and varying independence levels.
Evacuation Procedures for Residents with Mobility Limitations
Identify residents needing assistance (wheelchairs, walkers, bedbound, cognitive impairment). Assign evacuation partners and practice routes regularly. Map two exits per area and keep doors unlocked. For non-ambulatory residents, use wheelchairs, evacuation chairs, or blanket carriers, never leave anyone behind. For cognitive impairment, use simple language and assign a staff member to stay with them. Establish an assembly point outside, far enough for fire truck access, and brief residents during drills.
Shelter-in-Place Procedures and Assembly Areas
Identify interior shelter areas (bathrooms, hallways, basements for high winds, upper floors for flooding). Stock with flashlights, batteries, first aid, water, medications, communication devices, blankets, and resident lists. Practice shelter-in-place drills twice yearly.
Creating and Maintaining an Assisted Living Emergency Contact List
Your emergency contact list must be current, organized, and accessible to staff during a crisis.
Information to Include for Each Resident
Document for each resident: legal name, DOB, medical conditions, medications, allergies, clinician and pharmacy contact, emergency contacts, healthcare power of attorney, DNR status, preferred hospital, insurance, and communication needs. Store in a printed binder accessible to staff and a secure digital file. Update immediately when information changes.
Communication Protocols with Families and First Responders
Specify: Emergency coordinator or medical responder calls 911 with resident status and facility address. Emergency coordinator or communicator notifies families immediately for serious emergencies, within 24 hours for minor issues. Provide clear updates on status, treatment, and expected return. Document all calls with names, times, and content.
Staff Training, Drills, and Readiness
Protocols on paper mean nothing if staff don’t know them. Training and practice turn protocols into muscle memory.
Required Training Components and Frequency
Every staff member should receive training on:
- Your facility’s emergency preparedness plan
- Their specific role in an emergency
- Medical emergency response (first aid, CPR, when to call 911)
- Fire safety and evacuation procedures
- Shelter-in-place procedures
- How to communicate with residents and families during an emergency
- How to document incidents
Training frequency:
- Initial training before the staff member works alone with residents
- Annual refresher training for all staff
- CPR and First Aid certification every two years
- Additional training when protocols change
Document all training. Keep records showing who was trained, when, and what was covered. This satisfies regulatory requirements and proves your facility takes emergency preparedness seriously.
Conducting Effective Emergency Drills
Drills reveal what works and what doesn’t.
Fire evacuation drill: Conduct at least twice yearly. Simulate different times of day (morning, evening, night).
Medical emergency drill: Role-play a cardiac event or choking.
Shelter-in-place drill: Move all residents to shelter areas. Practice communication, resource management, and staying calm.
After each drill: Debrief with staff. What went well? What was confusing? What needs to change?
Include residents in drills when appropriate. Familiarity reduces fear during a real emergency.
Emergency Supplies, Equipment, and Continuity of Care
When an emergency strikes, you need supplies immediately. You can’t wait for delivery.
Essential Supplies and Backup Systems
Stock your facility with:
- First aid supplies (bandages, gauze, tape, antibiotic ointment, pain relief)
- CPR equipment (AED, CPR barrier masks)
- Emergency medications (epinephrine auto-injectors for severe allergies if residents have prescriptions)
- Oxygen if residents require it
- Blood pressure cuff and thermometer
- Flashlights and extra batteries
- Battery-powered or hand-crank radio
- Bottled water (one gallon per person per day, three-day supply minimum)
- Non-perishable food
- Blankets and coats
- Battery-powered phone chargers
- Two-way radios for staff communication if phone lines fail
- Generator or backup power for refrigerated medications
Check supplies quarterly. Replace expired items. Maintain a log of what you have and when it expires.
Backup systems:
- Keep a list of all residents’ medications printed and updated monthly
- Store medical records in a waterproof, portable container
- Have a backup plan for residents who need refrigerated medications (coolers with ice packs)
- Know where to get emergency supplies if your facility is damaged
Managing Medications and Medical Records During Emergencies
Medications are critical. Residents taking blood pressure medication, insulin, or heart medication can’t skip doses without serious consequences.
Before an emergency:
- Keep a current list of each resident’s medications, dosages, and frequency
- Store this list in a waterproof container
- Photograph or scan medication bottles
- Know which medications must be kept cool
- Have extra doses of critical medications on hand
During an emergency:
- If evacuation is needed, grab the medication list and any portable medications
- If residents are transported to a hospital, provide the medication list to paramedics
- Contact the resident’s pharmacy to request emergency refills if medications are lost
After an emergency:
- Coordinate with the resident’s clinician to resume normal medication schedules
- Replace any lost medications
- Update medical records
Post-Incident Documentation and Quality Improvement
What happens after the emergency is over matters as much as the response itself. Documentation protects residents, staff, and your facility. It also reveals how to improve.
Incident Reporting Requirements
Document every emergency, even minor ones. Your incident report should include:
- Date and time of incident
- Resident’s name and room number
- What happened (be specific and factual)
- Who was present
- What assessment was done
- What action was taken (called 911, contacted clinician, provided first aid)
- Who was contacted (family, clinician, emergency services)
- Time of each action
- Outcome (resident transported, treated on-site, monitored)
- Resident’s condition at time of report
- Staff member’s signature and title
Store incident reports securely. Review them for patterns. Did the same resident fall repeatedly? Did staff miss something? Use this information to prevent future incidents.
Recovery Planning and Plan Review
After an emergency, your facility needs time to recover. A recovery plan addresses:
- Resident care continuity (medications, meals, activities)
- Staff support (debriefing, counseling if traumatic)
- Family communication (updates on resident status)
- Facility repairs or restoration
- Regulatory reporting (some emergencies must be reported to licensing agencies)
Plan review: At least annually, review your entire emergency preparedness plan. Update it based on:
- Drills and what you learned
- Staff feedback
- Changes in resident population or medical needs
- Regulatory changes
- Lessons from other facilities’ incidents
Share the updated plan with all staff. Train them on changes.
Medical emergencies in assisted living demand preparation, clear thinking, and coordinated action. The protocols you put in place now determine how your facility responds when seconds count. At Providence Assisted Living Solutions, we prioritize resident safety through detailed planning, regular staff training, and honest evaluation of what works. Our small, intimate setting allows us to know each resident’s specific needs and tailor our emergency response accordingly.
Frequently Asked Questions
What is the first action a caregiver should take in a medical emergency?
Assess the resident’s responsiveness and breathing immediately. If the resident is unresponsive or experiencing severe symptoms like chest pain, difficulty breathing, or loss of consciousness, call 911 right away. For conscious residents with less severe symptoms, contact the resident’s clinician for guidance on whether emergency transport is needed. Always stay calm, keep the resident comfortable, and monitor their condition until help arrives or the clinician advises next steps.
What should an assisted living emergency preparedness plan include?
A comprehensive emergency preparedness plan must cover hazard identification, evacuation and shelter-in-place procedures, staff roles and training requirements, resident-specific care needs and mobility considerations, communication protocols with families and first responders, emergency supply inventories, medication and medical record management, and incident reporting procedures. The plan should be documented in writing, reviewed annually, and updated whenever resident needs or facility operations change.
How often should assisted living staff conduct emergency drills?
Facilities typically conduct fire drills and evacuation drills regularly. Many facilities also conduct tabletop exercises for medical emergencies and other scenarios at least twice yearly. Drills should involve all staff shifts and test different scenarios to ensure readiness. Document completion, identify gaps, and use findings to improve procedures and training.
What information should be on an assisted living emergency contact list?
Each resident’s emergency contact list should include family members and emergency contacts with phone numbers, the resident’s primary clinician and specialist contacts, preferred hospital or emergency facility, insurance information, medication list, known allergies, advance directives or healthcare power of attorney designee, and any special care needs or mobility limitations. Keep copies both in the resident’s file and accessible to staff during emergencies, and update it whenever information changes.
Recent Post

Big News! Providence Assisted Living Solutions

State Long-Term Care Ombudsman Program
May 12, 2026


Our Friendly Staff
May 27, 2026
